You sleep and still wake up tired. A walk that used to be easy leaves you wiped out for the rest of the day. Your thinking feels slow, your muscles ache for no reason, and every cold seems to take weeks to shake off. When someone suggests your mitochondria might not be working well, it can sound vague or even like a sales pitch. It’s neither. Mitochondria are the parts of your cells that turn food into usable energy, and when they slow down, almost every system in your body feels it. The good news is that in most people this slowdown is a state the body has moved into, and states can change.
What your mitochondria actually do
Almost every cell in your body contains mitochondria, often hundreds or thousands of them. Their main job is to take what you eat (sugar, fat and protein) and, using oxygen, turn it into ATP, the energy currency your cells spend on everything they do. Cells that work hardest carry the most: heart, muscle, brain, liver and kidney cells are packed with them. Red blood cells are the exception and have none.
Making energy is only half the story. Your mitochondria are also part of your cells’ alarm system. They are often the first part of a cell to notice a threat such as an infection or a toxin, and when they do, they deliberately change how the cell runs to protect it. This is known as the cell danger response.¹ I’ll come back to why that matters, because it changes how you think about low energy.
If you’d like the detail on how energy is actually produced, I’ve covered it in how your mitochondria make NADH and ATP.
Mitochondrial disease and mitochondrial dysfunction are not the same thing
These two terms get mixed up, and the difference matters.
Mitochondrial disease is a group of inherited conditions caused by faults in the genes that build mitochondria. Those faults can sit in the mitochondria’s own small set of DNA or in the main DNA in the cell nucleus. Together they affect roughly 1 in 4,300 adults, which makes them less rare than many people assume.² They are diagnosed by specialists with genetic testing, and they often show up in childhood with muscle weakness, developmental delay or neurological problems.
Mitochondrial dysfunction is different. It describes mitochondria that are structurally fine but working below capacity, because of what they are being exposed to or deprived of. It isn’t a formal diagnosis, and there’s no single test for it. It is a pattern, and in most people it can improve once the reasons behind it are addressed.
What mitochondrial dysfunction can feel like
Because every organ depends on mitochondria, the signs are spread across the whole body:
- Fatigue that rest doesn’t fix
- Crashing after physical or mental effort, sometimes a day later
- Brain fog and poor concentration
- Muscle aches, weakness or cramping without obvious cause
- Slow recovery from illness
- Poor tolerance of alcohol, chemicals or medications
- Feeling cold, or struggling to regulate temperature
Each of these has many possible causes, and none of them on its own means your mitochondria are the problem. It’s the combination, and the way they cluster after an illness or a long stretch of stress, that makes me look more closely.
Where it shows up
Reduced mitochondrial function turns up alongside chronic fatigue, fibromyalgia, insulin resistance and type 2 diabetes, heart disease and neurodegenerative conditions. In most of these it is one part of the picture rather than the single cause, and in many it’s still unclear which comes first.
Autism is a good example of why the detail matters. In 2019 I wrote that mitochondrial dysfunction sits behind many cases of autism, and that overstated it. About 5% of autistic children meet the criteria for true mitochondrial disease, far higher than in the general population. A much larger group, roughly a third, show markers of strained energy production such as raised lactate.³ So it is common enough to be worth looking for, without being the explanation for every child.
Why your mitochondria slow down
This is the part I most want you to take away. When your mitochondria slow down, it is often not because they’re broken. It’s because they’ve been told to.
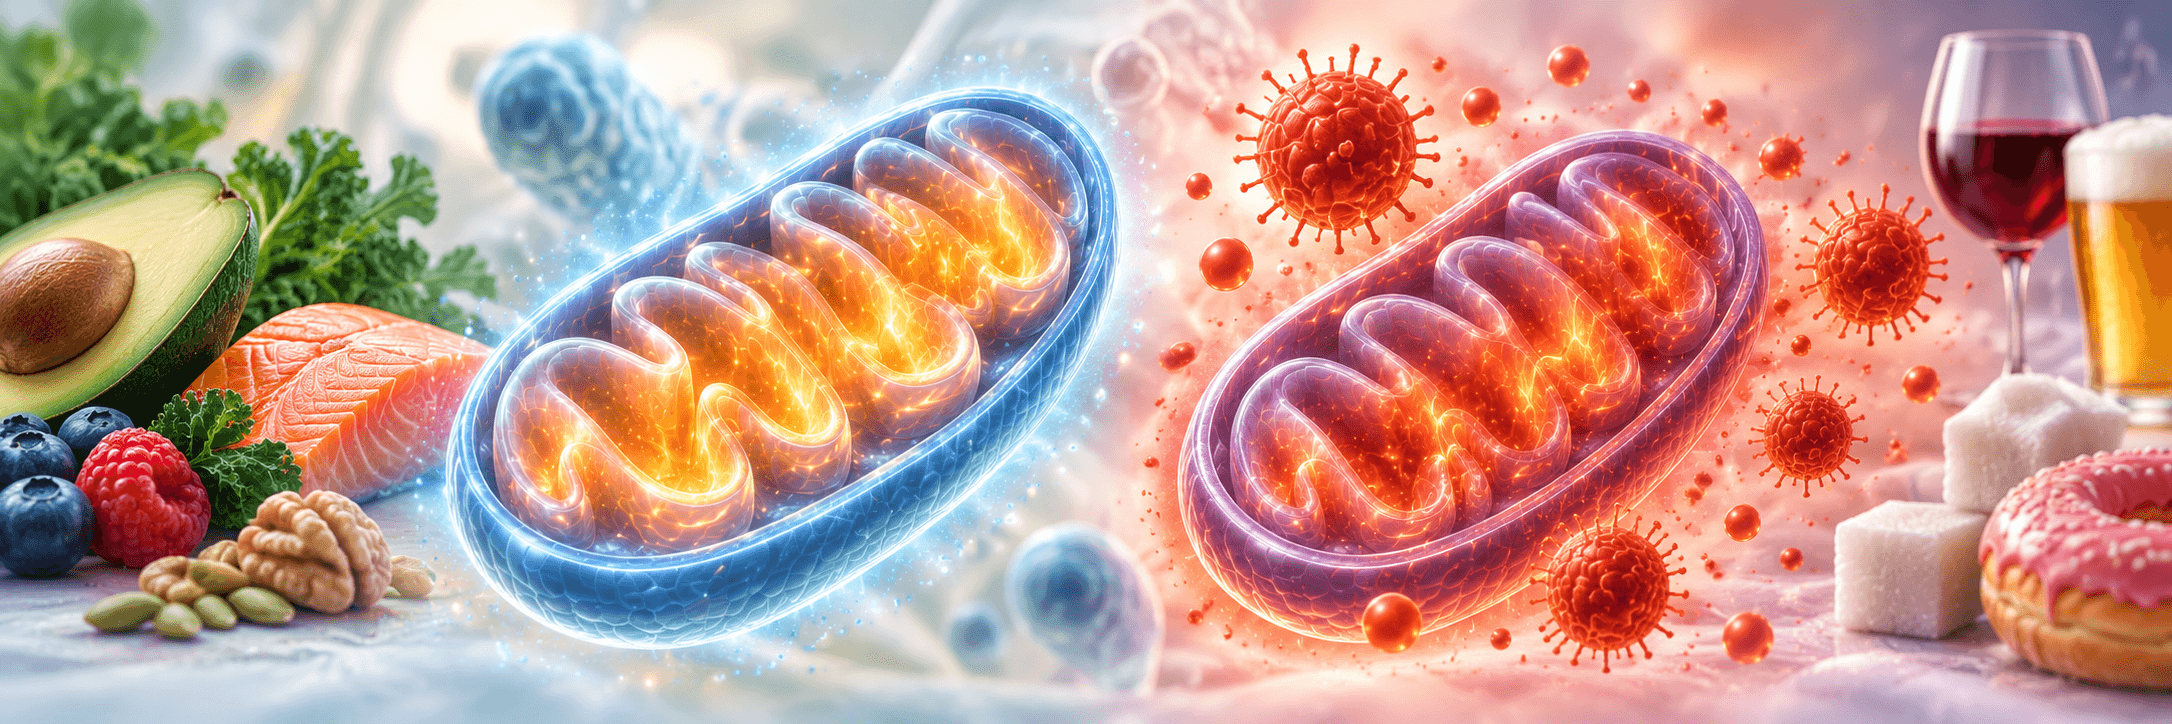
When a cell senses danger, through infection, toxins, injury or ongoing inflammation, its mitochondria shift into protection mode. They make less energy on purpose, because a cell running at full power is easier for a virus to use and more vulnerable to damage. That’s the cell danger response.¹
Free radicals are a big part of why. Making energy always produces some free radicals as a by-product, the way a fire produces sparks. During an infection, your immune cells also make free radicals deliberately, as weapons against the invader. Mitochondria sense this rising oxidative stress and turn their own energy production down, so they don’t add more sparks to a fire that is already burning hot.¹ Slowing down protects the cell from damaging itself. When free radical production keeps outpacing your antioxidant capacity, the brakes stay on.
It’s meant to be temporary. Trouble starts when the threat has passed but the alarm never switches off, and the body stays in a low-energy, defensive state for months or years. I’ve written more about this in mitochondria and the cell danger response.
This is also why pushing harder rarely works. If your cells are holding back energy to protect themselves, forcing more fuel or more effort into the system can make you feel worse. The better question is what is keeping the alarm on.
Common reasons include lingering infections, gut problems, mould and other toxin exposure, nutrient shortfalls, poor sleep, and a steady overload of sugar, alcohol and food that the mitochondria never get a break from.

NAD+: the molecule your energy depends on
One molecule sits at the centre of all this. NAD+ is a form of vitamin B3 that your mitochondria use to carry energy from food into the energy-making chain. Without enough of it, energy production slows no matter how much you eat. NAD+ is also used by enzymes that repair DNA and help cells cope with stress.
NAD+ levels fall as we age. Part of the reason is an enzyme called CD38, found on immune cells, which breaks NAD+ down and becomes more active with age.⁴ That decline is one reason NAD+ has become such a focus of anti-ageing interest, and why supplements claiming to raise it are everywhere.
Can NMN or NR supplements raise your NAD+?
NMN (nicotinamide mononucleotide) and NR (nicotinamide riboside) are building blocks your body can turn into NAD+. Taken by mouth, both reliably raise NAD+ levels in the blood, often to well above starting levels.⁵ That part is clear.
What is much less clear is whether that rise reaches the tissues that matter and changes how you feel. In the trials that took muscle samples, muscle NAD+ itself didn’t go up.⁵ The benefits reported so far are modest and come from small, short trials: some improvement in muscle strength in older men, better aerobic capacity in runners, and lower blood pressure in some studies.⁵ The strongest single result was in overweight women with prediabetes, whose muscles became more responsive to insulin after ten weeks on NMN.⁶
In short-term trials both have been well tolerated, but nobody yet knows the effects of taking them for years, and there is no established safe upper limit.⁵ If you are considering one, talk it through with a practitioner who knows your history. This isn’t a recommendation to take them.
Why your habits can cancel out what you put in
Think of your NAD+ as a bath. A supplement turns the tap up. But several everyday habits pull the plug out, and if the plug is out, a bigger tap doesn’t fill the bath.
- Alcohol. Every drink your liver processes converts NAD+ into its used form, NADH, in large amounts. That’s the main reason alcohol jams up energy production.⁷ I’ve walked through this step by step in what happens to your cells when you drink alcohol.
- Eating too much. Overloading your cells with fuel pushes NAD+ into its used form in the same way, just more slowly. In identical twins where one twin carried much more weight, the heavier twin’s fat tissue showed lower activity of the genes that make NAD+ and a trend towards more activity in the enzymes that use it up.⁸
- Inflammation. CD38, the enzyme that destroys NAD+, also breaks down NMN itself.⁴ So the more inflamed you are, the more of a supplement may be destroyed before your cells can use it.
- Not moving enough. Your muscles recycle most of their NAD+ using an enzyme called NAMPT, which declines with age. Twelve weeks of either aerobic or strength training rebuilt it in both young and older adults, with the biggest gains in the older group.⁹ Exercise doesn’t just burn energy. It rebuilds your capacity to make it.
To be honest about the evidence: nobody has directly tested whether drinking, overeating or inactivity cancels out NMN or NR in people. And the women in the most convincing trial benefited even though they were overweight with prediabetes, so the supplements aren’t useless in that setting. But each of these habits drains NAD+ through a known route, and in my clinical experience, people who fix the leaks first get far more from anything they add afterwards. A supplement on top of a lifestyle that keeps draining NAD+ is an expensive way to stand still.

What actually supports your mitochondria
- Move regularly, at a level you recover from. If effort leaves you crashed for days, start very small and build slowly. Pushing through a crash keeps the alarm on.
- Give your mitochondria breaks from fuel. Avoid constant grazing and very large meals, and keep sugar and refined carbohydrate in check.
- Keep alcohol low, especially while you’re recovering.
- Protect your sleep. Much of your cellular repair happens overnight.
- Look for what keeps the alarm on. Lingering infections, gut problems and toxin exposure are worth investigating rather than working around.
- Eat a varied diet with enough protein and B vitamins, since your mitochondria depend on a long list of nutrients to run.
Frequently asked questions
What are the signs of mitochondrial dysfunction?
The most common signs are fatigue that rest doesn’t fix, crashing after effort, brain fog, unexplained muscle aches and slow recovery from illness. These have many possible causes, so they’re a reason to look further rather than a diagnosis.
Is mitochondrial dysfunction the same as mitochondrial disease?
No. Mitochondrial disease is an inherited genetic condition diagnosed by specialists. Mitochondrial dysfunction describes mitochondria that are working below capacity because of infection, toxins, inflammation, nutrient gaps or lifestyle, and it can often improve.
Why do I feel so tired when I have an infection?
During an infection your immune system produces free radicals to fight it, and your mitochondria sense that oxidative stress and deliberately turn energy production down to protect your cells. The tiredness is part of the defence, and it should lift once the infection clears.
Can mitochondrial dysfunction be reversed?
In many people it can improve substantially once the reasons behind it are addressed. Because the slowdown is often a protective response, recovery usually depends on removing the threat rather than forcing more energy production.
Do NMN or NR supplements work?
Both reliably raise NAD+ in the blood. Evidence that they improve how people feel or function is still limited to small, short trials with modest results, and long-term safety is unknown.
Does alcohol lower NAD+?
Yes. Processing alcohol converts large amounts of NAD+ into NADH, its used form, which slows energy production in the liver and elsewhere for as long as alcohol is being cleared.
Does exercise increase NAD+?
Regular aerobic and strength training increase NAMPT, the main enzyme your muscles use to recycle NAD+, and can reverse its decline with age. If you crash after exertion, build up very gradually.
References
1. Naviaux RK. Metabolic features of the cell danger response. Mitochondrion. 2014;16:7-17. PMID 23981537.
2. Gorman GS, Schaefer AM, Ng Y, et al. Prevalence of nuclear and mitochondrial DNA mutations related to adult mitochondrial disease. Ann Neurol. 2015;77(5):753-759. PMID 25652200.
3. Rossignol DA, Frye RE. Mitochondrial dysfunction in autism spectrum disorders: a systematic review and meta-analysis. Mol Psychiatry. 2012;17(3):290-314. PMID 21263444.
4. Camacho-Pereira J, Tarragó MG, Chini CCS, et al. CD38 dictates age-related NAD decline and mitochondrial dysfunction through an SIRT3-dependent mechanism. Cell Metab. 2016;23(6):1127-1139. PMID 27304511.
5. Song Q, Zhou X, Xu K, et al. The safety and antiaging effects of nicotinamide mononucleotide in human clinical trials: an update. Adv Nutr. 2023;14(6):1416-1435. PMID 37619764.
6. Yoshino M, Yoshino J, Kayser BD, et al. Nicotinamide mononucleotide increases muscle insulin sensitivity in prediabetic women. Science. 2021;372(6547):1224-1229. PMID 33888596.
7. Cederbaum AI. Alcohol metabolism. Clin Liver Dis. 2012;16(4):667-685. PMID 23101976.
8. Jukarainen S, Heinonen S, Rämö JT, et al. Obesity is associated with low NAD+/SIRT pathway expression in adipose tissue of BMI-discordant monozygotic twins. J Clin Endocrinol Metab. 2016;101(1):275-283. PMID 26574954.
9. de Guia RM, Agerholm M, Nielsen TS, et al. Aerobic and resistance exercise training reverses age-dependent decline in NAD+ salvage capacity in human skeletal muscle. Physiol Rep. 2019;7(12):e14139. PMID 31207144.