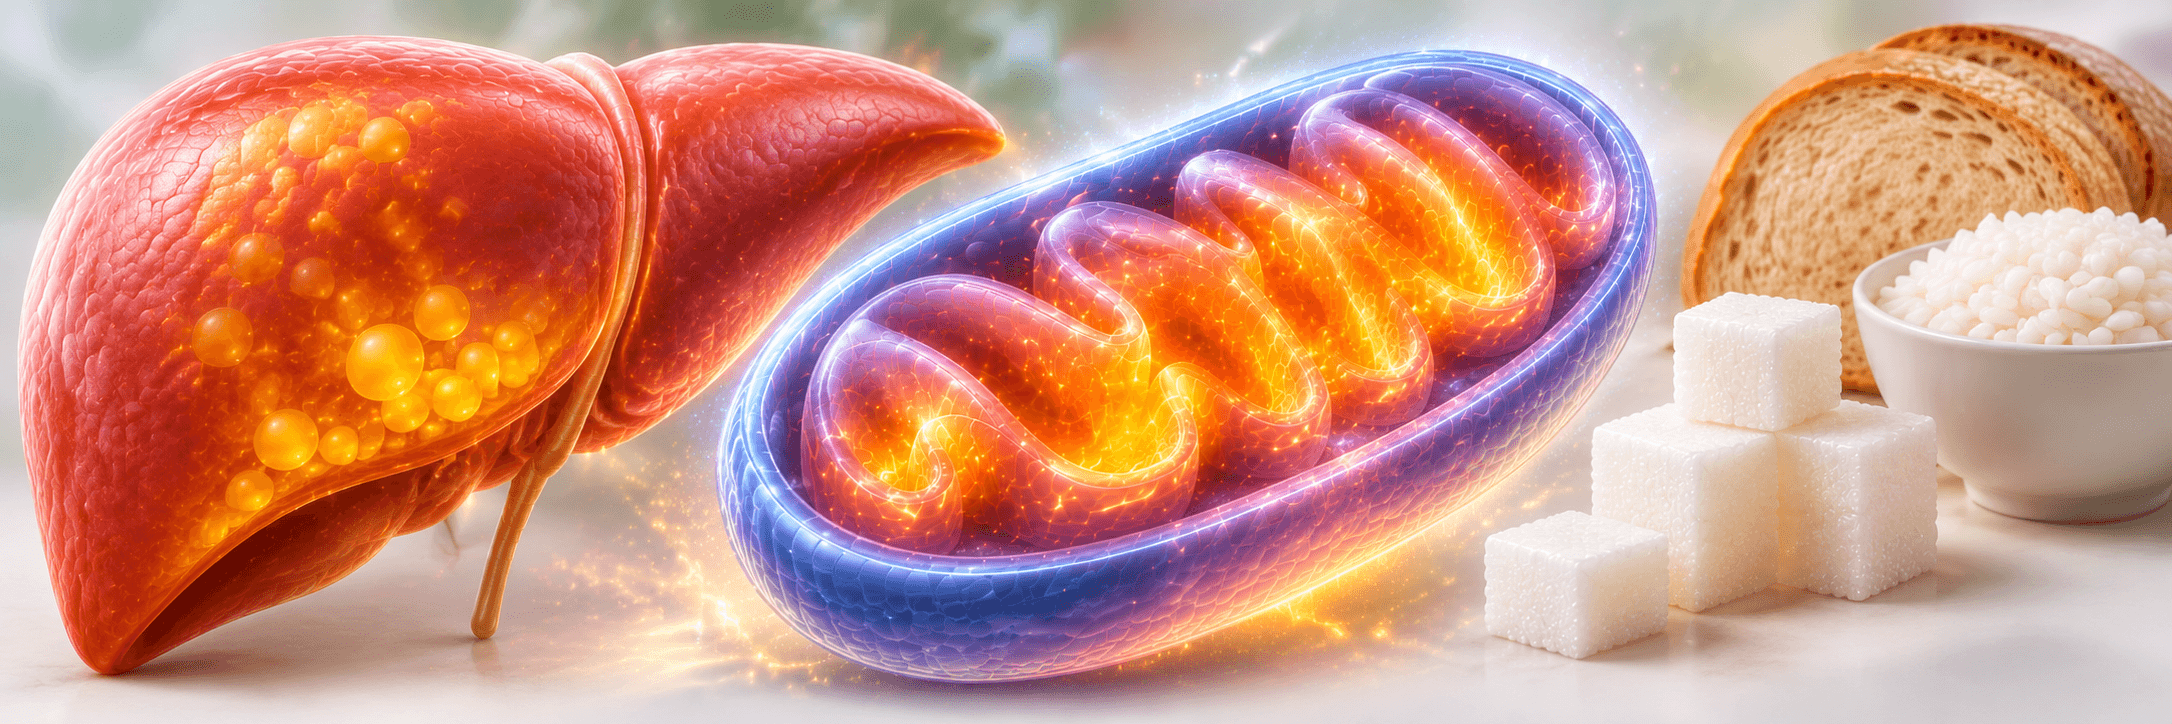
You’ve been told you have a fatty liver, or that your blood sugar, triglycerides and blood pressure are all creeping up together. Maybe you’re hungry an hour after eating, shaky if a meal is late, and the weight around your middle won’t shift no matter what you try. For years the blame went to dietary fat. The fuller story is that your liver turns excess sugar into fat, your mitochondria get swamped by more fuel than they can burn, and your cells start shutting their doors to protect themselves. Understanding that sequence changes what actually helps.
What metabolic syndrome and fatty liver are
Metabolic syndrome isn’t one disease. It’s a cluster of signs that tend to travel together, and you meet the definition if you have at least three of these five:¹
- A large waist (the cut-off depends on your sex and ethnic background)
- Triglycerides of 1.7 mmol/L or higher
- Low HDL cholesterol (below 1.0 mmol/L for men or 1.3 mmol/L for women)
- Blood pressure of 130/85 or higher
- Fasting blood glucose of 5.6 mmol/L or higher
Fatty liver is the liver’s version of the same problem, and it often comes first. Its name has recently changed. What used to be called non-alcoholic fatty liver disease is now called metabolic dysfunction-associated steatotic liver disease, or MASLD, because the driver is metabolic rather than simply “not alcohol”.²
How your liver turns sugar into fat
When you eat more sugar and starch than your body needs right away, your liver and muscles store the excess as glycogen. But glycogen storage is limited. Once those stores are full, your liver starts converting the extra sugar into fat, a process called de novo lipogenesis, which simply means “making fat from scratch”.
That fat is packaged into particles called VLDL and sent out into your blood as triglycerides. Whatever the liver can’t export stays in the liver, and that’s how fatty liver builds up. People with fatty liver make fat from scratch at a much higher rate. Around twice as much of their liver fat comes from this route compared with people with similar metabolic risk but a healthy liver, and it doesn’t switch off properly overnight.³
So sugar is a major driver. But fat isn’t off the hook, and I’ll come back to that.

Why you’re hungry an hour after eating
Three hormones manage your blood sugar. Insulin lowers it after a meal by helping sugar into your cells. Glucagon raises it between meals by telling your liver to release stored sugar. Cortisol and related stress hormones also raise it, so that you have fuel available to deal with a threat. That’s why ongoing stress keeps blood sugar higher than it should be.
Your liver also controls how much insulin is in your blood, because it clears a large share of the insulin your pancreas releases before it ever reaches the rest of your body. When the liver is fatty and insulin resistant, it clears less, so insulin levels stay higher for longer.⁴ Higher insulin pushes the liver to make even more fat, which makes the liver fattier, which reduces clearance further.⁴
The result after a sugary or starchy meal can be an overshoot: too much insulin, blood sugar dropping too fast, and then the crash. This is often called reactive hypoglycaemia, and it feels like:
- Hunger soon after eating
- Strong sugar or carbohydrate cravings
- Shakiness or jitteriness when a meal is late
- Mood swings, irritability or sudden anger
- Brain fog or tiredness after meals
Drowning the mitochondria
This is the part I most want you to understand, because it explains why so much of metabolic syndrome happens at once.
Your mitochondria burn fuel to make energy, but they can only handle so much at a time. When sugar and fat keep arriving faster than they can be burned, especially when both arrive together at the same meal, the mitochondria become overloaded. I call this drowning the mitochondria. In muscle cells of people with obesity-related insulin resistance, fat is pushed into the mitochondria faster than it can be fully burned. The Krebs cycle (their central energy engine) runs short of the components it needs, and the cell loses the ability to switch smoothly between burning fat and burning sugar.⁵
Several things happen when the mitochondria are drowning:
- Free radicals surge. Too much fuel pushed into the energy chain makes it leak electrons, creating free radicals. In people with high blood sugar, this mitochondrial free radical surge appears to be the common trigger behind much of the damage to nerves, blood vessels, eyes and kidneys.⁶
- Sugar is pushed into side roads. Sugar that can’t be burned is diverted into other pathways. One makes sorbitol, which builds up in nerves and the lens of the eye. Another produces advanced glycation end products, where sugar sticks to proteins and damages them.⁶
- Lactate builds up. When the mitochondria can’t take any more, sugar is turned into lactate instead. That’s one reason metabolic overload can show up as fatigue and muscle aches without exercise.
- Fat by-products build up in the wrong places. Fat that can’t be burned is stored inside muscle and liver cells, and some of its by-products interfere directly with insulin signalling.⁷ This is called lipotoxicity.
- Your antioxidants get used up. Glutathione and your other antioxidant defences are drawn down to deal with the free radical surge. Making glutathione depends on healthy methylation, which is one reason high homocysteine makes everything worse.
If you’d like the detail on how fuel moves through the mitochondria, I’ve covered it in sugar, fat or ketones: which gives your cells more energy.
Insulin resistance is your cells protecting themselves
Here’s the part that turns the usual story on its head. When a cell is already drowning in fuel, letting more sugar in would only make things worse. So the cell becomes less responsive to insulin. It is closing its doors.
Researchers in diabetes have argued that insulin resistance, particularly in people who are overweight, works as a defence mechanism that protects the heart and blood vessels from fuel overload. Overriding it by pushing in more insulin may cause harm, while reducing the fuel load is more likely to help.⁸ I see it as part of the same protective pattern as the cell danger response: the cell isn’t failing, it’s defending itself.
Not every organ can close its doors, though. Your liver and brain take up sugar without needing insulin, so they keep receiving the full load. For the liver, that means more fat-making and more fatty liver.

How this reaches your blood vessels
When the liver is overloaded, it sends out more VLDL, which raises your triglycerides. Over time this shifts the whole cholesterol picture: HDL falls, and LDL particles become smaller and denser. That combination is the pattern most strongly linked to heart disease in people with metabolic syndrome.
It helps to know what these names mean. HDL and LDL are not cholesterol themselves. They are carrier particles, made of protein and fat, that transport cholesterol and triglycerides around your body. Your “LDL cholesterol” result is a measure of the cholesterol being carried inside LDL particles.
So, sugar or fat?
The honest answer is both, and it depends on how much.
The evidence for cutting back sugar and refined carbohydrate is strong. When people with fatty liver ate a low-carbohydrate, higher-protein diet without eating fewer calories, their liver fat dropped quickly and dramatically within two weeks, fat-making in the liver fell, and fat burning rose.⁹
But fat isn’t harmless when you eat too much of it. When overweight adults ate an extra 1,000 calories a day for three weeks, the type of extra calories mattered. Extra saturated fat (butter, coconut oil, fatty meat) raised liver fat the most, by about 55%. Extra sugar raised it by about a third, by switching on fat-making. Extra unsaturated fat (olive oil, nuts, seeds) raised it the least.¹⁰
Putting those together:
- Reducing sugar and refined carbohydrate is one of the most effective things you can do for a fatty liver.
- Fat helps when it replaces sugar and starch, not when it’s added on top of a diet that’s already too rich.
- The worst combination for your mitochondria is lots of sugar and lots of fat at the same meal.
- Lean towards olive oil, nuts, seeds, avocado and oily fish, and use butter, ghee and coconut oil in moderation rather than in large amounts.
- Alcohol adds to the same overload. I’ve explained how in what happens to your cells when you drink alcohol.
- Regular movement gives your mitochondria somewhere to send the fuel. Leaving gaps between meals gives them time to clear the backlog.
What about statins?
Many people with metabolic syndrome are prescribed a statin, so it’s worth being clear about what statins do and don’t do. This is a contested area, and I want to give you both sides.
What statins do. Statins block the main enzyme your liver uses to make cholesterol. They lower LDL cholesterol. They don’t stop your liver turning sugar into fat, and they don’t treat insulin resistance or fatty liver.
The case for them. Lowering LDL with a statin reduces heart attacks and strokes, and the proportional benefit holds even in people at low risk.¹¹ The benefit is clearest in people who already have heart disease or are at high risk.
What often gets underplayed.
- The absolute benefit depends on your starting risk. If your risk of a heart attack is low to begin with, a proportional reduction translates into a small benefit for you personally. That’s a fair conversation to have with your doctor.
- Statins slightly raise the risk of developing diabetes. The relative increase is about 10% on low- and moderate-intensity statins and about 36% on high-intensity statins. The average rise in blood glucose is tiny. But most of the new diabetes cases occurred in people whose blood sugar was already at the high end of normal.¹² That’s exactly the group with metabolic syndrome.
- Statins lower CoQ10, because it’s made through the same pathway as cholesterol. Trials testing CoQ10 for statin-related muscle aches have reached conflicting conclusions.¹³˒¹⁴
- Statins modestly lower testosterone in both men and women.¹⁵
On the other side, muscle aches blamed on statins are often not caused by the statin itself. In people who had stopped statins because of side effects and were then given statin, placebo and no tablet in rotation, most of their symptoms appeared on placebo too.¹⁶
Where the weight of evidence sits: statins reduce cardiovascular events, most clearly in people at higher risk. The diabetes risk is real but small, and concentrated in people whose blood sugar is already borderline. Neither fact changes the bigger picture. A statin lowers one number, but it doesn’t address the overload that’s driving the fatty liver, the blood sugar and the triglycerides.
If you’re on a statin, please don’t stop it without talking to your prescriber. It’s reasonable to ask what your absolute risk is, and to have your fasting glucose and HbA1c checked regularly, especially if you already have signs of metabolic syndrome.
Frequently asked questions
What causes fatty liver if I don’t drink?
The main driver is more fuel than your body can use. Excess sugar and starch are converted into fat in the liver, and excess dietary fat, especially saturated fat, adds to it. Insulin resistance makes the liver keep making fat even when it doesn’t need to.
Is sugar or fat worse for a fatty liver?
Both contribute. Sugar switches on fat-making in the liver, and cutting carbohydrates reduces liver fat quickly. But when calories are in excess, saturated fat raised liver fat even more than sugar did. Fat helps when it replaces sugar, not when it’s added on top.
What does “drowning the mitochondria” mean?
It describes mitochondria receiving more sugar and fat than they can burn. The overload creates free radicals, pushes sugar into damaging side pathways and lactate, and leaves fat by-products in cells. Cells respond by becoming insulin resistant to keep more fuel out.
Why am I hungry soon after eating?
A fatty, insulin-resistant liver clears less insulin, so insulin can overshoot after a sugary or starchy meal. Blood sugar then drops too fast, triggering hunger, cravings, shakiness and irritability.
Can fatty liver be reversed?
In its early stages, yes. Reducing sugar and refined carbohydrate, avoiding excess calories, cutting back alcohol and moving regularly can lower liver fat quickly. More advanced stages with inflammation or scarring need medical monitoring.
Do statins cause diabetes?
Statins slightly increase the risk of developing diabetes, mostly in people whose blood sugar is already near the threshold. For people at high cardiovascular risk, the reduction in heart attacks and strokes usually outweighs this. Discuss your own risk with your prescriber rather than stopping on your own.
References
1. Alberti KGMM, Eckel RH, Grundy SM, et al. Harmonizing the metabolic syndrome. Circulation. 2009;120(16):1640-1645. PMID 19805654.
2. Rinella ME, Lazarus JV, Ratziu V, et al. A multisociety Delphi consensus statement on new fatty liver disease nomenclature. Hepatology. 2023;78(6):1966-1986. PMID 37363821.
3. Lambert JE, Ramos-Roman MA, Browning JD, Parks EJ. Increased de novo lipogenesis is a distinct characteristic of individuals with nonalcoholic fatty liver disease. Gastroenterology. 2014;146(3):726-735. PMID 24316260.
4. Najjar SM, Perdomo G. Hepatic insulin clearance: mechanism and physiology. Physiology (Bethesda). 2019;34(3):198-215. PMID 30968756.
5. Koves TR, Ussher JR, Noland RC, et al. Mitochondrial overload and incomplete fatty acid oxidation contribute to skeletal muscle insulin resistance. Cell Metab. 2008;7(1):45-56. PMID 18177724.
6. Brownlee M. The pathobiology of diabetic complications: a unifying mechanism. Diabetes. 2005;54(6):1615-1625. PMID 15919781.
7. Samuel VT, Shulman GI. Mechanisms for insulin resistance: common threads and missing links. Cell. 2012;148(5):852-871. PMID 22385956.
8. Nolan CJ, Ruderman NB, Kahn SE, Pedersen O, Prentki M. Insulin resistance as a physiological defense against metabolic stress: implications for the management of subsets of type 2 diabetes. Diabetes. 2015;64(3):673-686. PMID 25713189.
9. Mardinoglu A, Wu H, Bjornson E, et al. An integrated understanding of the rapid metabolic benefits of a carbohydrate-restricted diet on hepatic steatosis in humans. Cell Metab. 2018;27(3):559-571. PMID 29456073.
10. Luukkonen PK, Sädevirta S, Zhou Y, et al. Saturated fat is more metabolically harmful for the human liver than unsaturated fat or simple sugars. Diabetes Care. 2018;41(8):1732-1739. PMID 29844096.
11. Cholesterol Treatment Trialists’ (CTT) Collaborators. The effects of lowering LDL cholesterol with statin therapy in people at low risk of vascular disease: meta-analysis of individual data from 27 randomised trials. Lancet. 2012;380(9841):581-590. PMID 22607822.
12. Cholesterol Treatment Trialists’ (CTT) Collaboration. Effects of statin therapy on diagnoses of new-onset diabetes and worsening glycaemia in large-scale randomised blinded statin trials: an individual participant data meta-analysis. Lancet Diabetes Endocrinol. 2024;12(5):306-319. PMID 38554713.
13. Banach M, Serban C, Sahebkar A, et al. Effects of coenzyme Q10 on statin-induced myopathy: a meta-analysis of randomized controlled trials. Mayo Clin Proc. 2015;90(1):24-34. PMID 25440725.
14. Qu H, Guo M, Chai H, et al. Effects of coenzyme Q10 on statin-induced myopathy: an updated meta-analysis of randomized controlled trials. J Am Heart Assoc. 2018;7(19):e009835. PMID 30371340.
15. Schooling CM, Au Yeung SL, Freeman G, Cowling BJ. The effect of statins on testosterone in men and women, a systematic review and meta-analysis of randomized controlled trials. BMC Med. 2013;11:57. PMID 23448151.
16. Wood FA, Howard JP, Finegold JA, et al. N-of-1 trial of a statin, placebo, or no treatment to assess side effects. N Engl J Med. 2020;383(22):2182-2184. PMID 33196154.