For decades the story was simple: eat fat, cholesterol builds up in your arteries like grease in a pipe, and eventually the pipe blocks. If that were the whole story, cutting fat and lowering cholesterol would solve heart disease, and it hasn’t. Your arteries are living tissue, and plaque forms as a response to damage in the artery wall. Cholesterol is part of that story, but so are inflammation, blood sugar, your gut bacteria, methylation and how well your blood vessels can relax. Understanding how they fit together gives you far more to work with than a single number on a blood test.
How plaque actually forms
The inside of every artery is lined with a thin layer of cells called the endothelium. When it’s healthy, it’s smooth, it keeps blood flowing freely, and it controls what passes into the artery wall.
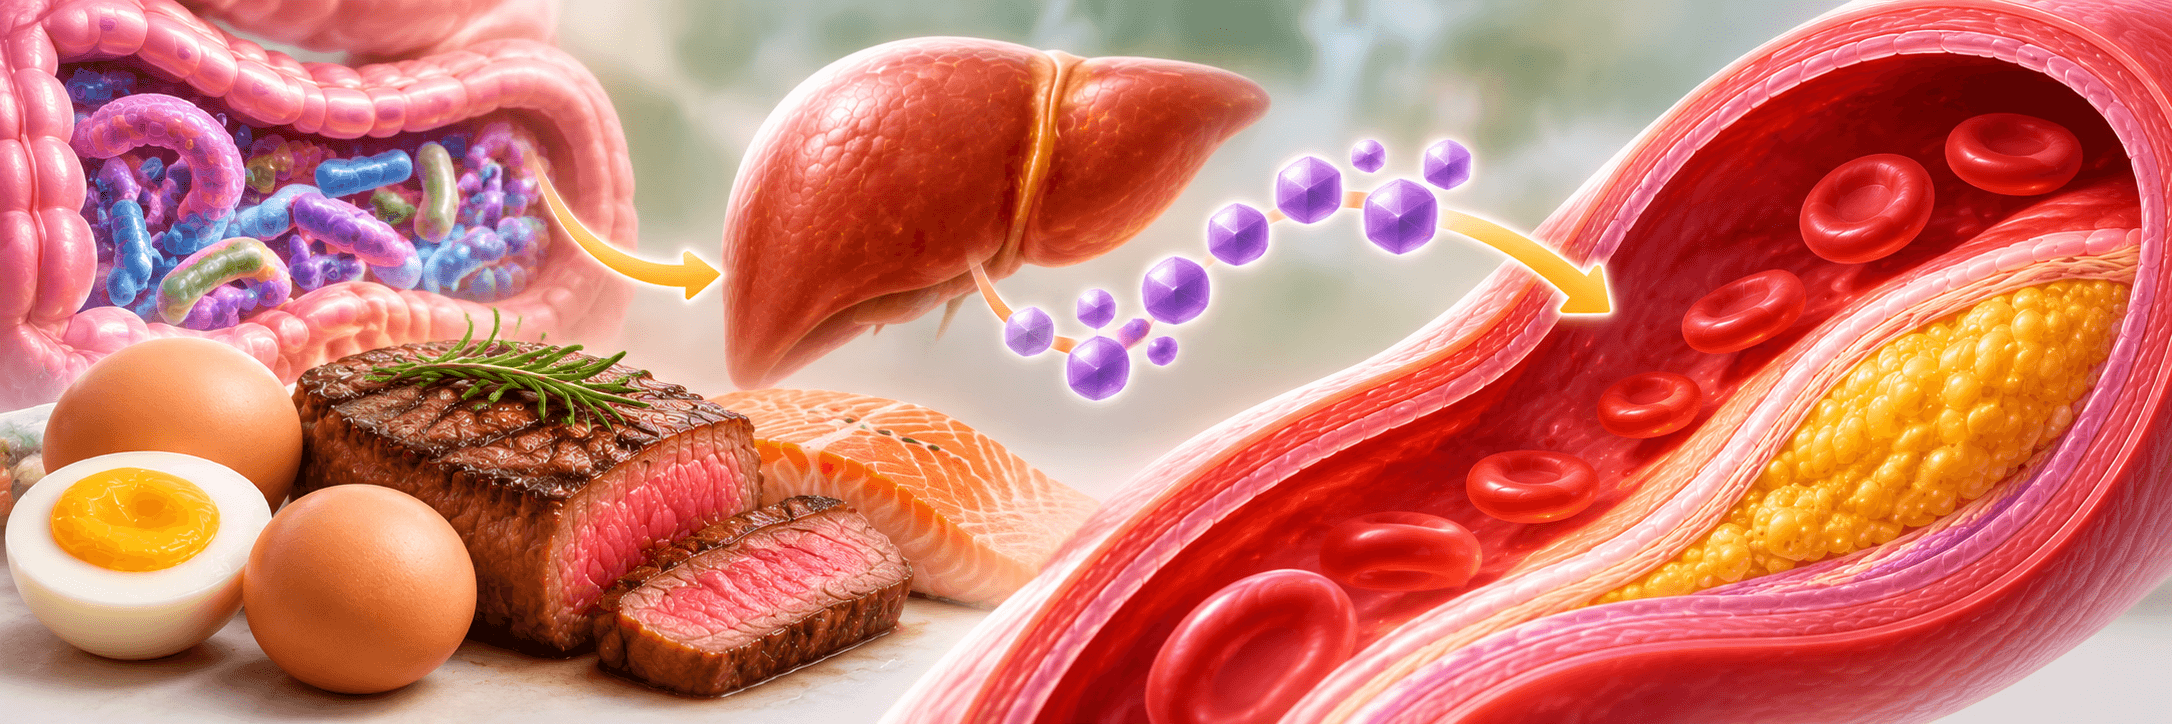
Plaque starts when that lining is damaged. High blood sugar, high blood pressure, smoking, oxidative stress and ongoing inflammation all injure it. LDL particles, which carry cholesterol through your blood, slip into the damaged wall and get stuck. There they become oxidised. Your immune cells arrive to clean up, swallow the oxidised LDL and swell into what are called foam cells. Over time, foam cells, inflammation, scar tissue and calcium build up into a plaque.¹
Atherosclerosis is now recognised as an inflammatory disease of the artery wall, not simply a plumbing problem.¹

Cholesterol or inflammation?
This is one of the most argued-about questions in heart health, so here are both sides.
The case for LDL. The evidence that LDL particles cause atherosclerosis is strong. People born with genes that give them lower LDL have less heart disease over their lifetime, people born with very high LDL develop it early, and lowering LDL with medication reduces heart attacks in proportion to how far it falls.²
The case for inflammation. In a large trial in people who had already had a heart attack, a drug that reduced inflammation without changing cholesterol at all lowered the rate of further heart attacks and strokes.³ That shows inflammation drives events independently of LDL.
Where the weight of evidence sits: both are true at once. LDL particles are the raw material of plaque, so the more of them there are, the more can get into the wall. But inflammation, oxidation and damage to the lining decide how much harm they do once they’re there. That’s why I think of atherosclerosis as a problem of cellular function, not only of cholesterol levels.
TMAO: is red meat the problem?
Choline (found in eggs, liver and meat) and carnitine (found mainly in red meat) are both important nutrients. Choline helps build cell membranes and supports methylation, and carnitine carries fat into your mitochondria to be burned.
Some of the choline and carnitine you eat is converted by gut bacteria into a compound called TMA. Your liver then converts TMA into TMAO. In mice, TMAO speeds up atherosclerosis, and in people, higher TMAO levels go along with more heart attacks and strokes.⁴˒⁵˒⁶ This research is a big part of why red meat and eggs have been blamed for heart disease.
But there’s a lot this story leaves out:
- Your gut bacteria decide how much TMAO you make. When people ate carnitine, meat eaters produced far more TMAO than vegans and vegetarians, because they carried different gut bacteria.⁵ The same food produces very different amounts of TMAO in different people.
- Fish raises TMAO far more than meat. When men ate fish, their TMAO rose roughly 50 times more than after eating eggs or beef, because fish already contains TMAO.⁷ Yet fish is consistently linked with better heart health, not worse.
- TMAO may be a marker rather than a cause. Genetic studies that can test cause and effect found no sign that higher TMAO causes heart disease. They did find that type 2 diabetes and kidney disease raise TMAO.⁸ So high TMAO may be flagging metabolic and kidney trouble that is itself driving heart disease.
My view hasn’t changed since I first wrote this: meat isn’t the problem on its own. The state of your gut and your metabolic health matter more than whether meat is on your plate.

FMO3: the enzyme that makes TMAO
The liver enzyme that converts TMA into TMAO is called FMO3. It’s a flavin enzyme, so it depends on vitamin B2 (riboflavin). Women tend to have more FMO3 activity than men. In mice, testosterone switches FMO3 down, and bile acids switch it up.⁹
That raises an interesting possibility, and this part is my own interpretation rather than something tested in people. If testosterone keeps FMO3 lower, then falling testosterone with age might let FMO3, and TMAO, rise. It’s a question worth asking rather than an answer.
FMO3 also explains the fishy-smell question. If you notice a fishy body or breath odour after eating eggs, fish or choline-rich foods, that’s TMA that your liver hasn’t converted. It usually points to FMO3 not keeping up, which in its most marked form is a genetic condition called trimethylaminuria, rather than to a gut problem alone.
Choline is needed, not the enemy
Cutting out choline to avoid TMAO can backfire. Your liver needs choline to package fat into VLDL particles and send it out. Without enough, fat gets stuck in the liver, and choline deficiency is a well-established cause of fatty liver.¹⁰ I’ve explained how fatty liver feeds into heart disease in whether sugar or fat is to blame for fatty liver.
Choline is also a back-up source of methyl groups. When folate or B12 is low, your body leans harder on choline for methylation, drawing it away from building cell membranes and exporting fat. So low folate and B12 can quietly increase your choline needs.
Nitric oxide: what keeps your arteries flexible
Healthy arteries can widen and narrow as needed, and nitric oxide is what lets them relax. The endothelium makes it using an enzyme called eNOS, and exercise is one of the strongest signals for it.
Your diet supplies a second route. Leafy greens and beetroot are rich in nitrate. Bacteria on your tongue convert nitrate into nitrite, which your body can then turn into nitric oxide.¹¹ Antiseptic mouthwash can kill those bacteria and blunt this route.¹¹ (In 2019 I wrote that the nitrogen in leafy greens comes from amino acids. It’s actually nitrate, and it works through this mouth-bacteria pathway.)
There is also a natural brake on nitric oxide called ADMA. It’s released when proteins that have been tagged with methyl groups are broken down, and it competes with the raw material eNOS needs. In young adults with high cholesterol, ADMA levels were more than double those of people with normal cholesterol, and their arteries relaxed less well. When researchers raised the balance back in favour of eNOS’s raw material, the arteries recovered.¹² So in those people the enzyme wasn’t broken. It was being blocked.
Homocysteine
High homocysteine has long been linked with heart disease, and it reflects how well your methylation is working. But here’s an honest complication. In large trials, lowering homocysteine with B vitamins didn’t reduce heart attacks, though it slightly reduced strokes.¹³ So homocysteine is better treated as a sign that methylation is struggling than as a target on its own. I’ve explained why high homocysteine makes everything worse.
Why women’s risk rises after menopause
Oestrogen (estrogen) helps keep LDL receptors active on liver cells, and those receptors pull LDL out of your blood. As oestrogen falls at menopause, LDL rises. That rise happens around the menopausal transition itself, beyond what you’d expect from getting older.¹⁴ It’s one reason women’s heart disease risk catches up with men’s after menopause, and why cholesterol results that were fine for years can change quite suddenly.
The antioxidant trade-off
Here’s a connection I find important, and it’s my own interpretation. Your cells use the same molecule, NADPH, both to build cholesterol and to recycle glutathione, your main antioxidant. When the liver is overloaded by sugar, alcohol or overeating, more NADPH is spent on building fat and cholesterol, and less may be left to protect tissues like the artery lining from oxidation. Since oxidised LDL is what turns into plaque, that trade-off could matter. I’ve covered the biochemistry in sugar, fat or ketones: which gives your cells more energy.
What about statins?
Statins lower LDL by blocking the enzyme your liver uses to make cholesterol. The same pathway also makes CoQ10, which your mitochondria need, and that’s why statins lower CoQ10 levels.
The mainstream view: lowering LDL with statins reduces heart attacks and strokes, and the proportional benefit holds even in people at low risk.¹⁵ The absolute benefit is largest for people at high risk.
The critics’ view: some researchers argue that statins may worsen artery calcification and heart muscle function, partly through lowering CoQ10.¹⁶
What the evidence shows on calcification: statins do increase the calcium in plaque, even as they shrink the plaque overall.¹⁷ Cardiologists read this as plaque being stabilised and less likely to rupture. Critics read it as harm. It does mean that a rising coronary calcium score on a statin isn’t necessarily a sign it’s failing.
On balance, the trial evidence that statins reduce heart attacks is strong, especially for people at higher risk. But they don’t address inflammation, blood sugar, the gut or methylation, which is why they’re one tool and not the whole answer. I’ve covered the diabetes risk and the other side effects in the fatty liver article. If you’re on a statin, please don’t stop it without talking to your prescriber.
What protects your arteries
- Move every day. Exercise boosts nitric oxide production and improves your cholesterol profile.
- Eat leafy greens and beetroot for nitrate, and go easy on antiseptic mouthwash.
- Cut back sugar and refined carbohydrate to reduce blood sugar damage to the artery lining and overload in the liver.
- Look after your gut bacteria with a varied, fibre-rich diet, since they influence how much TMAO you make.
- Keep choline, folate, B12 and B2 adequate through food, so methylation and liver fat export keep working.
- Know your blood pressure and don’t smoke. Both directly damage the artery lining.
Frequently asked questions
What causes atherosclerosis?
Atherosclerosis starts when the inner lining of an artery is damaged by high blood sugar, high blood pressure, smoking, oxidative stress or inflammation. LDL particles get trapped in the damaged wall, become oxidised and attract immune cells, which build up into plaque over time.
Is atherosclerosis caused by cholesterol or inflammation?
Both. LDL particles are the raw material of plaque, and the evidence that they cause atherosclerosis is strong. Inflammation and damage to the artery lining decide how much harm they do, and reducing inflammation lowers heart attacks even without changing cholesterol.
Does red meat cause heart disease through TMAO?
Gut bacteria turn carnitine from red meat into TMA, which the liver converts into TMAO. But how much TMAO you make depends on your gut bacteria, fish raises TMAO far more than meat, and genetic studies suggest TMAO may be a marker of diabetes and kidney disease rather than a direct cause.
Why do I smell fishy after eating eggs or fish?
A fishy odour usually means TMA isn’t being converted into odourless TMAO by the liver enzyme FMO3. In its marked form this is a genetic condition called trimethylaminuria, and it’s worth discussing with your doctor.
What is nitric oxide and why does it matter for arteries?
Nitric oxide relaxes blood vessels, keeping arteries flexible and blood pressure down. Your artery lining makes it, exercise increases it, and nitrate from leafy greens and beetroot provides a second source through bacteria in your mouth.
Why does cholesterol rise after menopause?
Oestrogen helps keep the liver’s LDL receptors active. When oestrogen falls at menopause, fewer LDL particles are cleared from the blood, so LDL cholesterol rises, beyond what ageing alone would explain.
References
1. Ross R. Atherosclerosis: an inflammatory disease. N Engl J Med. 1999;340(2):115-126. PMID 9887164.
2. Ference BA, Ginsberg HN, Graham I, et al. Low-density lipoproteins cause atherosclerotic cardiovascular disease. 1. Evidence from genetic, epidemiologic, and clinical studies. A consensus statement from the European Atherosclerosis Society Consensus Panel. Eur Heart J. 2017;38(32):2459-2472. PMID 28444290.
3. Ridker PM, Everett BM, Thuren T, et al. Antiinflammatory therapy with canakinumab for atherosclerotic disease. N Engl J Med. 2017;377(12):1119-1131. PMID 28845751.
4. Wang Z, Klipfell E, Bennett BJ, et al. Gut flora metabolism of phosphatidylcholine promotes cardiovascular disease. Nature. 2011;472(7341):57-63. PMID 21475195.
5. Koeth RA, Wang Z, Levison BS, et al. Intestinal microbiota metabolism of L-carnitine, a nutrient in red meat, promotes atherosclerosis. Nat Med. 2013;19(5):576-585. PMID 23563705.
6. Tang WHW, Wang Z, Levison BS, et al. Intestinal microbial metabolism of phosphatidylcholine and cardiovascular risk. N Engl J Med. 2013;368(17):1575-1584. PMID 23614584.
7. Cho CE, Taesuwan S, Malysheva OV, et al. Trimethylamine-N-oxide (TMAO) response to animal source foods varies among healthy young men and is influenced by their gut microbiota composition: a randomized controlled trial. Mol Nutr Food Res. 2017;61(1). PMID 27377678.
8. Jia J, Dou P, Gao M, et al. Assessment of causal direction between gut microbiota-dependent metabolites and cardiometabolic health: a bidirectional Mendelian randomization analysis. Diabetes. 2019;68(9):1747-1755. PMID 31167879.
9. Bennett BJ, de Aguiar Vallim TQ, Wang Z, et al. Trimethylamine-N-oxide, a metabolite associated with atherosclerosis, exhibits complex genetic and dietary regulation. Cell Metab. 2013;17(1):49-60. PMID 23312283.
10. Corbin KD, Zeisel SH. Choline metabolism provides novel insights into nonalcoholic fatty liver disease and its progression. Curr Opin Gastroenterol. 2012;28(2):159-165. PMID 22134222.
11. Lundberg JO, Weitzberg E, Gladwin MT. The nitrate-nitrite-nitric oxide pathway in physiology and therapeutics. Nat Rev Drug Discov. 2008;7(2):156-167. PMID 18167491.
12. Böger RH, Bode-Böger SM, Szuba A, et al. Asymmetric dimethylarginine (ADMA): a novel risk factor for endothelial dysfunction: its role in hypercholesterolemia. Circulation. 1998;98(18):1842-1847. PMID 9799202.
13. Martí-Carvajal AJ, Solà I, Lathyris D, Dayer M. Homocysteine-lowering interventions for preventing cardiovascular events. Cochrane Database Syst Rev. 2017;8(8):CD006612. PMID 28816346.
14. Matthews KA, Crawford SL, Chae CU, et al. Are changes in cardiovascular disease risk factors in midlife women due to chronological aging or to the menopausal transition? J Am Coll Cardiol. 2009;54(25):2366-2373. PMID 20082925.
15. Cholesterol Treatment Trialists’ (CTT) Collaborators. The effects of lowering LDL cholesterol with statin therapy in people at low risk of vascular disease: meta-analysis of individual data from 27 randomised trials. Lancet. 2012;380(9841):581-590. PMID 22607822.
16. Okuyama H, Langsjoen PH, Hamazaki T, et al. Statins stimulate atherosclerosis and heart failure: pharmacological mechanisms. Expert Rev Clin Pharmacol. 2015;8(2):189-199. PMID 25655639.
17. Puri R, Nicholls SJ, Shao M, et al. Impact of statins on serial coronary calcification during atheroma progression and regression. J Am Coll Cardiol. 2015;65(13):1273-1282. PMID 25835438.